Category: Articles

  • Should We Be Worried About Zombie Pathogens?

    Should We Be Worried About Zombie Pathogens?

    In the summer of 2016, Arctic regions such as Siberia and Greenland were hit with an unusual heat wave. As plants grew and water levels rose, a thick layer of permafrost that had accumulated from winters prior began to thaw, revealing something extremely concerning: anthrax-infected reindeer carcasses (Fox-Skelly, 2017).

    That summer a 12-year-old boy in rural Siberia died of anthrax. Dozens of people were hospitalized for the same disease (Goudarzi, 2016). The region had not seen a surge in anthrax cases for over 75 years—so what brought on the sudden outbreak?

    The consensus amongst researchers and Russian officials was that it was caused by the thawing of permafrost (the frozen layer of soil underneath ice and snow) induced by unusually high temperatures. The region saw temperatures around 35 degrees Celsius that summer, or 95 degrees Fahrenheit—much warmer than the usual ten degrees Celsius (Goudarzi, 2016). The warmer the weather the deeper the thaw, potentially releasing decades-old microorganisms from the soil. These microorganisms could be anything from harmless amoeba-consuming “giant” viruses to long-eradicated pathogens such as the smallpox virus—unfortunately in this case, what was unearthed were the carcasses of reindeer that had died from anthrax, allowing the pathogen to leech into food stores and water sources.

    As soon as this story broke out, media outlets took it and ran with it. Suddenly we were faced with what seemed to be a new existential threat to humanity: ancient bacteria and viruses frozen in the ground, coming “back to life” as the earth continues to warm from climate change. “Zombie” pathogens that lied dormant in the ground would infect humans with bygone diseases such as 1918 influenza, smallpox, and bubonic plague. While the idea of dormant bacteria re-infecting humans is terrifying, how valid is it and how concerned should we really be?

    In 2014, evolutionary biologists Jean-Michel Claverie and Chantal Abergel at the Aix-Marseille University in France were able to revive a giant virus, Pithovirus sibericum, that had been dormant in ice for 30,000 years. The virus is 1.5 micrometers long—the largest ever found (Yong, 2014). While it is infectious, its preferred hosts are amoebas and are harmless to humans. This discovery has prompted both the researchers and general public alike to acknowledge the possibility that other more dangerous viruses may also be capable of resurfacing as the Arctic continues to warm.

    However, it’s important to note that Claverie and Abergel’s research pertains to viruses that target amoebas, not ones that targets humans (Doucleff, 2018). While P. sibericum may have been evolutionarily equipped to survive in frozen soil, that may not be the case for viruses responsible for influenza or smallpox that had evolved to thrive in warm human flesh.

    Another piece of information to consider is that Bacillus anthracis, the bacteria that causes anthrax infections, seeping out from the soil and infecting animals is not new. In fact, there are French accounts of anthrax-laden fields wiping out entire flocks of sheep dating back to the medieval period, until Louis Pasteur developed a vaccine against B. anthracis in 1881 (Jones, 2010).

    It’s not as if researchers haven’t tried to revive decades-old human-infecting viruses. There have been multiple attempts to revive the 1918 influenza and smallpox viruses using tissue samples from well-preserved arctic mummies, with varying degrees of success. While the attempt to isolate a living 1918 influenza virus proved unsuccessful, a Russian attempt to revive smallpox did result in their recovering parts of the virus (Taunbenberger, Hultin, & Morens, 2007; Doucleff, 2018).

    At the present moment, the threat of another outbreak of smallpox or Spanish flu is unlikely. These viruses are maladapted to the cold and unable to survive without a warm mammalian host. We may not known what the future holds as climate change uncovers more microorganisms from newly thawed soil, but perhaps we should be more concerned about what goes on in the lab with our attempts to revive long-dead viruses, rather than fixate on the idea of zombie pathogens.

    —

    References

    Doucleff, M. (2018). Are there zombie viruses in the thawing permafrost? https://www.npr.org/sections/goatsandsoda/2018/01/24/575974220/are-there-zombie-viruses-in-the-thawing-permafrost

    Fox-Skelly, J. (2017). There are diseases hidden in ice, and they are waking up. http://www.bbc.com/earth/story/20170504-there-are-diseases-hidden-in-ice-and-they-are-waking-up

    Goudarzi, S. (2016). What lies beneath. Scientific American, 315, 11-12.

    Jones, S. D. (2010). Death in a Small Package: A Short History of Anthrax. Johns Hopkins University Press.

    Taubenberger, J. K., Hultin, J. V., & Morens, D. M. (2007). Discovery and characterization of the 1918 pandemic influenza virus in historical context. Antiviral therapy, 12(4 Pt B), 581–591.

    Yong, E. (2014). Giant virus resurrected from 30,000-year-old-ice. https://www.nature.com/news/giant-virus-resurrected-from-30-000-year-old-ice-1.14801#/ref-link-1


  • Concussions can affect youth

    Concussions can affect youth

    From a young age, many children take up sports like football, boxing, and soccer. Playing such sports can potentially have a huge negative effect if a child or teenager experiences a concussion while playing their game. Depending on the person, the damage could have a lasting effect.

    According to the Mayo Clinic, a concussion is a traumatic brain injury that affects your brain with certain effects being headaches, memory problems and balance problems (Mayo Clinic, 2019). A concussion itself could have a lasting impression on many different children and teenagers. Certain effects of a concussion that could be long term are light sensitivity, photophobia, vertigo, depression, and many more symptoms (“Long Term Effects”, 2018). Although these symptoms are pretty short term, you could potentially have long term effects when you are older, but it can have a significant impact when an individual is still young and their brain is still developing. In a study in Sweden between 1973 and 1985 that observed individuals who had head injuries of people under 25. In these studies, the researchers observed that these people were more likely to have mental health care and not able to graduate or attend college than a person who did not have this injury. Not only that, the individual also had a greater chance of dying prematurely (Reynolds, 2016). Therefore, it is important to know the potential risks of allowing ones’ children in playing such sports.

    With the continuous increase of popularity of sports with young children and teenagers, the likelihood of having a concussion has increased. Approximately 1.6 – 3.8 million sports/recreation-related concussions occur each year within the United States (“What is a concussion”, 2019). With the amount of concussions that occur, there are a large number that occur within individuals who are younger than 20. The Blue Cross Blue Shield reported that there was a 71% increase in the number of concussions for individuals under the age of 20 from the years 2010 to 2015 (“The steep rise”). With the practice of such sports, these are slowly leading to concussions. In the United States, the competitive sports with the most reported concussions is football and it accounts for more than 60% of concussions (“What is a concussion”, 2019). Football is one of the major sports that causes the concussion in males as well and it is one of the major sports that causes concussions from 5 – 18 years. Football itself has caused the most concussion in high school sports and the incident rates of having a concussion was .60 per 1000. In female sports, the most amount of concussions occur in soccer (“Which Youth Sports”). With these specific sports causing concussions in the youth, it is our duty to educate and provide safer measures to help younger people to essentially play the sport in safe manner without any injuries or concussions occurring due to lack of precaution.

    In order to prevent concussions, we as a community need to help those younger understand the risks at hand and allow them to understand the problems with doing such. Essentially have protective headgear when playing a sport that may have cause someone to hit their head is a big thing. Specifically, in soccer, it would be a wise thing to do play with a head gear could prevent some injuries according to specific ratings released by the Virginia Tech Helmet Lab (Staff, 2018). Having such protective measures will allow the youth to develop and prevent them from having certain effects as they grow older.


    Clinic, M. (2019, March 16). Concussion. Retrieved from https://www.mayoclinic.org/diseases-conditions/concussion/symptoms-causes/syc-20355594

    Reynolds, G. (2016, October 5). A Single Concussion May Have Lasting Impact. Retrieved from https://www.nytimes.com/2016/10/05/well/move/a-single-concussion-may-have-lasting-impact.html.

    Long Term Effects of Post Concussion Syndrome. (0AD). Retrieved from https://www.theraspecs.com/blog/long-term-effects-post-concussion-syndrome/

    staff, S. X. (2018, May 2). Could soccer headgear reduce concussion risk? First-ever ratings say yes. Retrieved from https://medicalxpress.com/news/2018-05-soccer-headgear-concussion-first-ever.html.

    The steep rise in concussion diagnoses in the U.S. (0AD). Retrieved from https://www.bcbs.com/the-health-of-america/reports/the-steep-rise-concussion-diagnoses-the-us.

    What is a Concussion? (2019). Retrieved from http://www.protectthebrain.org/Brain-Injury-Research/What-is-a-Concussion-.aspx

    Which Youth Sports Cause the Most Concussions? (n.d.). Retrieved from https://www.medstarsportsmedicine.org/research/which-youth-sports-cause-the-most-concussions/.

  • Health Shot: Vaccines

    Health Shot: Vaccines


    I’m sure we can all remember that dreaded moment at the doctor’s office when they say “Time for some shots!”. Much crying later (maybe that’s just me) , we leave the office with a brightly colored band aid – and sometimes a sticker for the road. But what exactly goes on in these shots we receive from such a young age? What do these vaccinations do in our bodies? Moreover, what explains the origins of the the anti-vax movement?

    What happens when we get sick?

    When bacteria and viruses enter the body, immune cells called help fight off these invaders, which are called antigens. These antigens trigger the response by the body to fight them off with T Cells and B Cells. B Cells make antibodies, which are proteins produced by our immune system that help attack the antigens. Each antibody fits like a puzzle piece with a particular antigen and blocks off the antigen from communicating with other cells. This causes the antigen to die off. T Cells secrete chemical signals in the body that let other immune responses know to activate. Once the body has begun to eliminate the microbes faster than they reproduce, and the disease is eliminated, some of the T and B cells convert into memory cells can recognize the infectious microbe if it appears again and appropriately release antibodies. This offensive cycle of recognize, react, and remember allows our body to be very effective in responding to bacteria and viruses we interact with every day.

    How do vaccines help?

    Vaccines allow the body to be exposed to an illness and developed the memory cells, so that when we are exposed again to the microbe, we can quickly react. The vaccine contains a weakened form of the virus that does not cause the disease or reproduce very well – but this enough to get our bodies into action. Following the same cycle as above, the body fights off this weakened disease and is left with the memory T and B cells that cause future protection. Since the disease is in weakened form, many vaccines require more than one dose. In the case of the flu vaccine, the CDC recommends a vaccination every year since the vaccination is updated each year to include the strains that research suggests would be most pervasive that flu season.

    Where did the Autism-Vaccine link come from?

    In 1998, Andrew J Wakefield along with 12 co-authors published a study suggesting that from 12 cases, they found links between the MMR vaccination and autism in The Lancet. Though the paper could not support a causal relationship between the MMR vaccination and autism, in a video Wakefield suggested that the risk of autism was developing with the combined MMR vaccines. The press reaction to the publication and Wakefields statements were immediate, and parents in Britain and the United States began to delay vaccinations for their children.

    Ideas Debunked:

    In 2004, the editor of the Lancet revealed that the Wakefield has been paid by attorneys looking to file lawsuits against vaccine manufacturers, demonstrating a clear conflict of interest and ulterior motive. In 2010, after many of the co-authors had redacted their statements in the paper, The Lancet redacted the paper itself.

    In 2011, The British Medical Journal published a report by Brian Deer who investigated how Wakefield could have made the statements he did in the 1998 paper. Deer found that while the paper claimed eight children showed autism-like symptoms days after the vaccination, in fact only two showed symptoms that they had even before the vaccine was administered. With all this evidence, researchers agree that the original study should not have been published as the results could be categorized as research fraud.

    After the MMR-Autism hypothesis was no longer held, critics cited thimerosal, a preservative containing mercury as a possible cause for autism. In the late 1990’s concern for eating mercury present in a different form in fish heightened, and people turned their eyes to the mercury used in vaccines. A final report published in 2004 by the Institute of Medicine rejected an association between thimerosal and autism. However, today most childhood vaccines no longer contain thimerosal.

    Since autism rates have continued to increase since the onset of routine vaccination, critics continue to question vaccines. Research from the Autism Speaks associate reveals that autism is causes by both genetic and environmental factors. The exact reason why autism develops is still unclear, but vaccinations have been currently ruled out as a cause.

    The Anti-Vax Movement:

    In 2007, celebrity Jenny McCarthy’s son was diagnosed with Autism, and she blamed the diagnosis on the effect of vaccinations. This essentially kickstarted the recent anti-vax movement again, though the movement has been in existence since vaccines were widespread. The recent advent of Facebook and twitter has increased the spread of misinformation and has increased vaccines refusal across America. With the popularity of the anti-vax movement, the herd immunity of our population is threatened. For highly contagious diseases, herd immunity is achieved when 90-95% of the population is vaccinated. For less contagious diseases, like polio, 80-85% is enough. Herd immunity is precisely why anti-vax movement affect those who still choose to get immunized. Turning into a Tragedy of the Commons, one  misinformed individual can affect the health safety of their surrounding community. For this reason, staying informed with well established facts, rather than opinions, is important when dealing with medical issues.

    Sources:

    Vaccines Protect Your Community. (2017, December). Retrieved March 10, 19, from https://www.vaccines.gov/basics/work/protection

    How Do Vaccines Work? (2019, April 09). Retrieved from https://www.niaid.nih.gov/research/how-vaccines-work

    Understand how Vaccines work. (2018, July). Retrieved from https://www.cdc.gov/vaccines/hcp/conversations/downloads/vacsafe-understand-color-office.pdf

    Do Vaccines Cause Autism? (n.d.). Retrieved from https://www.historyofvaccines.org/content/articles/do-vaccines-cause-autism

    Wakefield, A. J. (1999). MMR vaccination and autism. The Lancet,354(9182), 949-950. doi:10.1016/s0140-6736(05)75696-8


  • Computer Programming: A Women’s History

    Computer Programming: A Women’s History

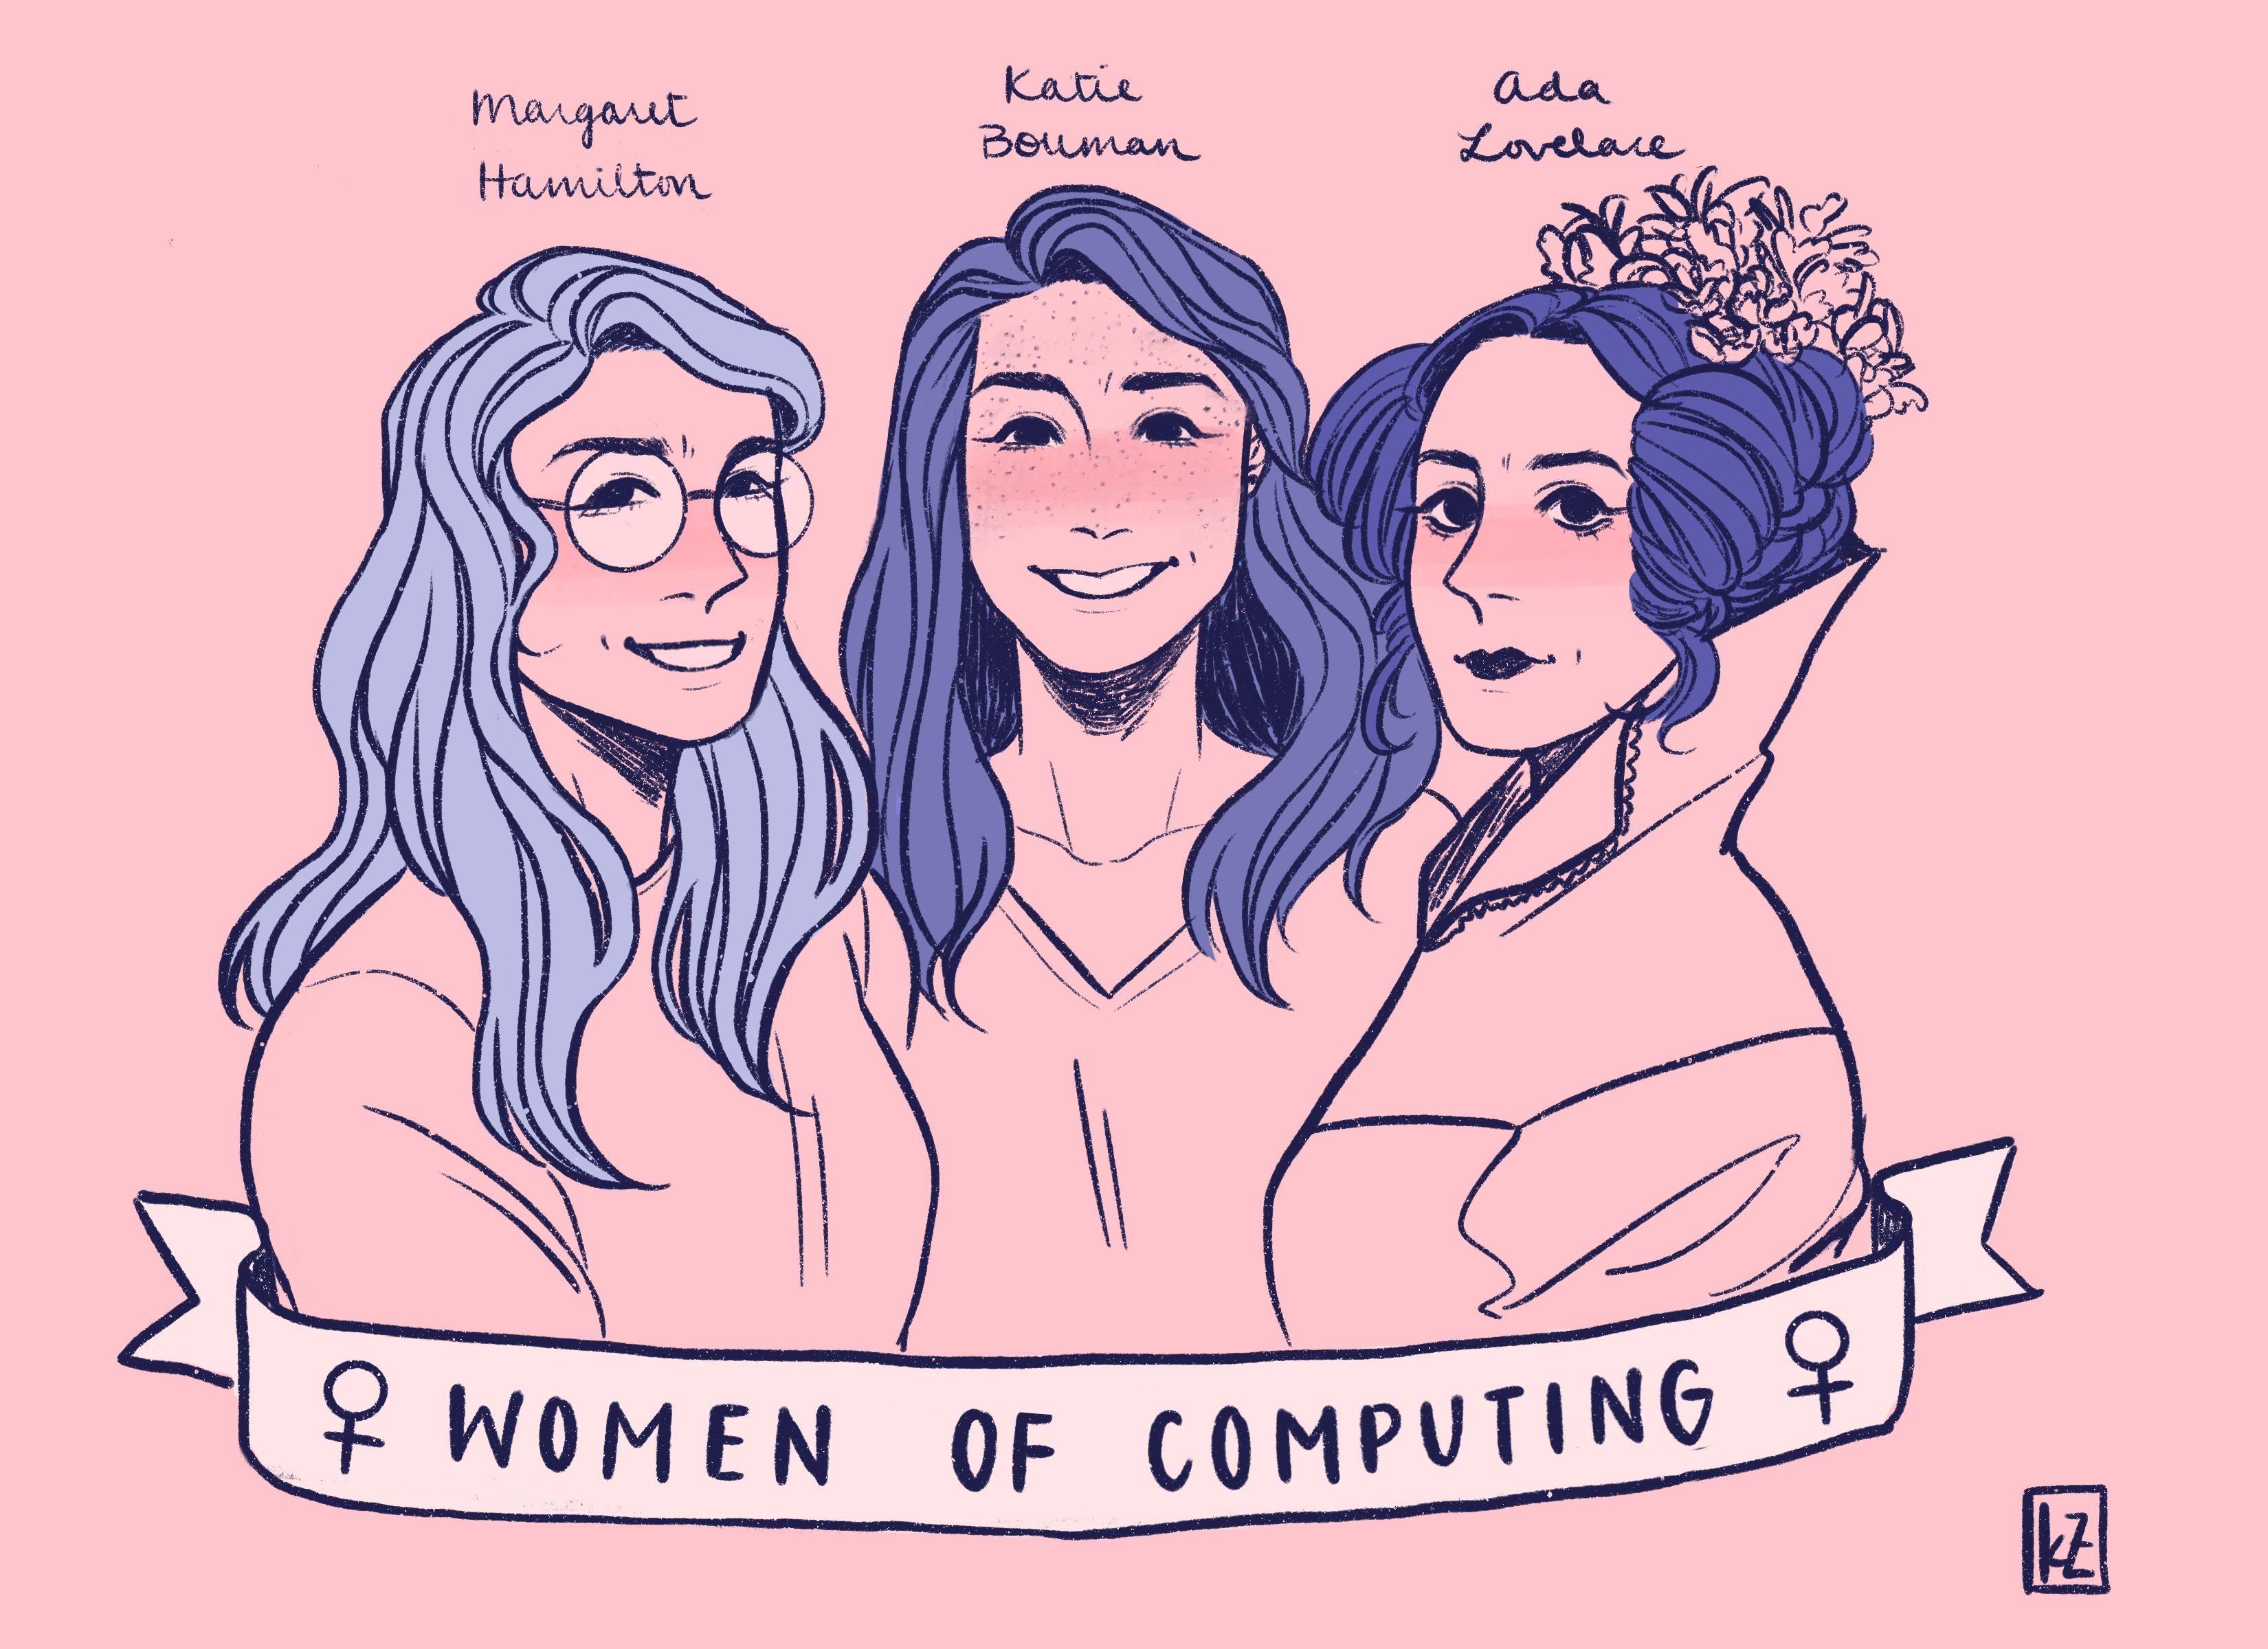
    I always found it interesting how people tend to see computer science and coding in general as inherently a male-dominated field, despite how the very foundations of computer programming were established by a woman, Ada Lovelace. In the 60s, computer programming was considered women’s work (look at the work of Dorothy Vaughan). The code that send us to the moon was predominantly written by a woman, Margaret Hamilton. In fact, in the days of the Atari and early gaming systems, many legendary game developers were also women (Carol Shaw, Donna Bailey, and Roberta Williams, just to name a few). And today, MIT’s Katie Bouman and her team are the first to ever capture an image of a black hole. Computer science may appear to be a male-dominated field, but we can’t forget that the pioneers of the field were women. This is my tribute to just three of those extraordinary female programmers.

  • Hidden Figures Beyond: Alexa Canady, the First African-American Neurosurgeon

    Hidden Figures Beyond: Alexa Canady, the First African-American Neurosurgeon

    This article will be the first of a series of articles I hope to continue called Hidden Figures Beyond. The goal of this series is to go beyond the movie Hidden Figures, highlighting more scientists that are underrepresented minorities whose research and studies continue to make an impact on the discovery of knowledge today. The first scientist that I will be highlighting is the first African-American neurosurgeon in America, Alexa Canady. She is retired now, but I would like to discuss her history with neurosurgery and the research that she focused on and its impact.

    To give a quick description of her early life, Alexa Canady was born in Lansing, Michigan to Elizabeth Hortense Canady and Clinton Canady Jr. Her mother was an educator and her father was a dentist, so she and her brother grew up in an education-based environment. Her family always emphasized the importance of education, especially as an African-American woman, which motivated her to graduate from her high school with honors and to attend the University of Michigan to earn. However, like most college students, she had her fair share of struggles as well. As a mathematics major, she had a ‘crisis of confidence’, questioning her place at the University of Michigan. When she learned about a minority scholarship for medicine, she felt an instant connection and decided to pursue it, thus switching her major to zoology and earning her bachelor’s degree in 1971, then graduating cum laude from medical school there in 1975. After graduating, she interned at Yale-New Haven Hospital for a year, where she still faced discrimination, being told on her first day, “You must be our new equal opportunity package.” Despite this, she continued to strive and be voted as one of the top interns by the physicians on her staff.

    After her internship, she had her residency at the University of Minnesota from 1976 to 1981, when she started a fellowship at Children’s Hospital in Philidelphia. In 1982, she completed her fellowship and was soon hired onto the faculty of Detroit’s Henry Ford Hospital. She worked there until she was hired as the chief of pediatric neurosurgery at the Children’s Hospital of Michigan in 1987. Canady specialized and researched in life-threatening illnesses, congenital spinal abnormalities, and other brain injuries like hydrocephalus, trauma and brain tumors. She performed many life-saving treatments on thousands of patients, most of her patients being ten years or younger. During her time in Detroit, she researched at Wayne State University to improve neurosurgical technology with two other neuroscientists. This research led to the development of an antisiphon shunt that helps to treat hydrocephalus, an abnormal accumulation of fluid inside the brain. She continued this work until her partial retirement in 2001, retiring to Florida. During this time, she worked as a part-time surgeon until her complete retirement in 2012. Even though Canady is retired, she is still a full-time role model for African-Americans interested in STEM, and working on the issues of medical bias of African-American patients.


    As I learned more and more about Alexa Canady and what an amazing scientist she is, I was also a little sad about the fact that she really isn’t very well known, even though she has done so much and has saved the lives of so many people. She’s stated that she doesn’t want the attention, but she is an inspirational role model and now that I know about her story, I don’t think I ever want to forget about her and her legacy. I’d like to leave this quote from a recent interview of hers when she was asked why young students should pursue neuroscience to perfectly define her life and legacy.

    “It’s fun to make people better… It’s intellectually challenging, you get kind of a high when everybody says ‘Ah the neurosurgeon is here.’”
    -Alexa Canady, 2017

  • Understanding the Use of CRISPR in Humans

    Understanding the Use of CRISPR in Humans

    CRISPR, an anacronym that stands for “clustered regularly interspaced short palindromic repeats,” is a concept becoming quite ubiquitous in most biology classes and rapidly gaining familiarity among experimental medicine and biology discussion circles not to mention scientific publications and health- or science-related news media. However, people who are not closely following these discussions or do not have a contemporary knowledge of genetics, understand very little about what exactly CRISPR could be or do. Even if one goes word by word for what each letter of the CRISPR anacronym stands for, it would be hard for the general public to have a workable idea of the science underlying this term. This article intends to provide an uncomplicate explanation of the concepts around CRISPR by resorting to a language that simplifies the ideas without decreasing the accuracy to the main concepts.

     Source: https://www.sciencenewsforstudents.org/article/crispr-enters-its-first-human-trials

    CRISPR vs. CRISPR Technology

    First, we may need to distinguish CRISPR, as a family of DNA sequences which is part of the immune system identified in bacteria cells, from CRISPR technology, as a tool to modify those DNA sequences in humans. Therefore, when scientists are talking about CRISPR and “trials in humans” they usually refer to a method used to modify the DNA genome in humans.

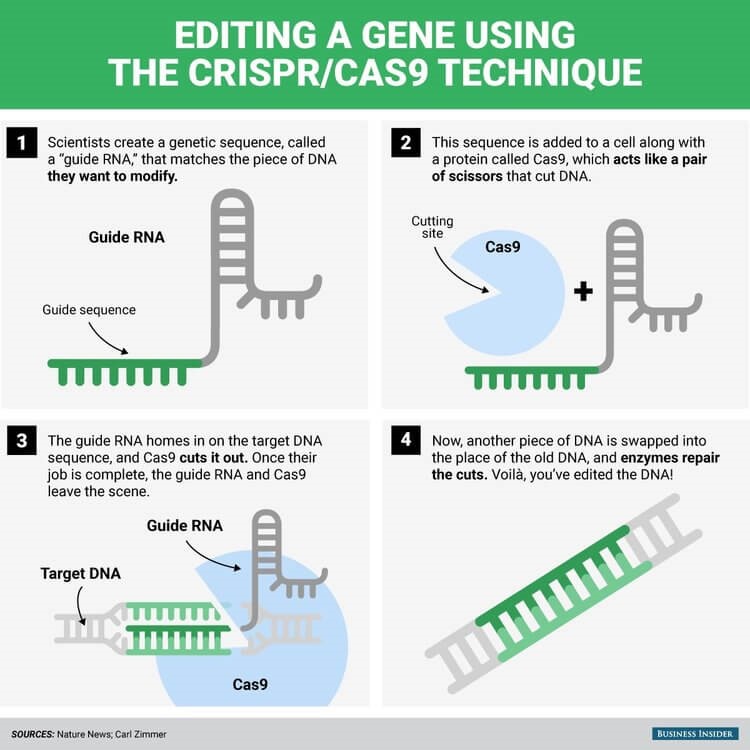
    CRISPR has two components: the Cas9 which is a protein that can unwind and cut DNA sequences and the guide RNA (or gRNA) that recognizes the sequence of specific sequence of DNA to be edited.  In some literature the CRISPR technology is also known as CRISPR/Cas9 in reference to a specific cutting protein – we will return to this concept below.

    At least, three important questions arise here: How well is our understanding of the DNA sequences in cells? How well developed and precise are the tools to manipulate those DNA sequences? Why do we need to modify any part of the DNA sequences? The first two questions are not only quite related, but also involve a lot of uncertainty even for scientist working everyday with CRISPR technology. The third question involves not only the diverse therapies and diagnostic purposes for which CRISPR technology is being used but also the dangers and ethical dilemmas involved in the use of this technology. We will mostly focus on the third question while bearing in mind and revisiting the first two questions.

    Source: https://sciencehook.com/biology/crispr-cas9-and-gene-editing-explained-140

    Understanding Gene Editing

    CRISPR is a system mostly known for the modification of DNA sequences to correct or delete any mutations or defect within the sequence of spaced DNA palindrome. In a practical way, it could be seen as spellcheckers of misspelled sequences and a cut-and-paste tool for DNA editing.  CRISPR has been used in cancer patients, people with blood disorder and other possible diseases or defects that CRISPR could help to identify and correct.

    To have a more precise idea lets return to the underlying concepts once more. The purpose of CRISPR technology is first to identify genes associated with CRISPR.  Particularly relevant are those genes that could produce enzymes or proteins named Cris9 which are able to unwind and cut DNA, which were identified in the laboratories of Jennifer Doudna and Emmanuelle Charpentier and for which they received the Nobel Prize in Medicine.

    With Cris9 at hand, it could be used to unwind and cut out specific strands of DNA (mostly those parts of the human genome that were previously identified as the mutations that cause unwanted defects or health problems). At that point, a specific gRNA is created to match that stretch of the DNA sequence that was cut.  Next, after the gRNA is being attached to the DNA cutting enzyme Cas9, the complex formed by the Cas9 and gRNA is re-introduced to the targeted cell where the defect was detected.  In other words, the enzyme cuts the strands of DNA at the specific human genome so that whatever is deleted can be properly replaced by a corrected part. In this case, researchers would remove some cells that are susceptible to a bacteria or virus or cells that show some unwanted mutation, modify the DNA in those cells and then put the modified cells back to potentially decrease the likelihood of a disease or defect.

    Hopes, Slow Progress and Concerns

    In general, CRISPR has been associated with a scientific revolution happening in medicine that would soon help us to better fight diseases, cure cancer, diagnose diseases or maybe even create new humans. The increasing understanding of how CRISPR works has given some hope and enthusiasm to scientist.  Therefore, it is now frequent to find news about CRISPR being used in experiments.

    However, we are in the early days of CRISPR and the progress is slow.  In spite of the hopes, CRISPR has been used solely in a limited number of well-known mutations that cause certain diseases. This is an important limitation for various reasons. The number of unknown mutations is still quite large compared to the few known ones.  Moreover, the mutations in the same place of the sequence of DNA of two individuals could be quite different and therefore the application of CRISPR to cut and correct such a mutation may work in some but not in all individuals. Even in the cases where the application of CRISPR in experiments with animals were relatively successful, for example the injection of corrected stem cells that let paralyzed rats walk again, when the same experiments were run in humans, they did not provide the same results.

    The slow progress has not stopped the development of theoretical and laboratory models where CRISPR could be use beyond unwinding and cutting DNA, but also as a pointer and diagnostic tool. In the future, it is expected that CRISPR could be used in developing advanced patient therapies, customized medications and even cure life-long inherited diseases.

    Ethical considerations

    However, when CRISPR is associated with the “trials in humans,” a number of natural legitimate ethical concerns have been risen around the use of CRISPR.  For example, it has become accepted the use in CRISPR in somatic cells such as T-cells to treat diseases, but when CRISPR is used in embryo or stem cells, it becomes controversial, mainly because genome modifications are done at germline level with unknown of unintended consequences for patients and future generations.  In simple terms, the issue is the corrections at germline of a DNA sequence that could be passed to future generations by introducing heritable changes to sperm, eggs or embryos without full consideration of the risks or proper understanding of the participants.

    Source: https://www.technologyreview.com/s/612997/the-crispr-twins-had-their-brains-altered/

    This issue gained big relevance when a He Jiankui, a Chinese scientist, worked in the germline to modify the genes in twin kids (before birth), aimed to make the twins immune to HIV. This experiment was considered quite irresponsible and ethically questionable leading to a worldwide condemnation of the scientific community; the risks to the babies were higher than the benefits for a number of reasons: the parents provided consent without being properly informed, the CRISPR experiment was kept secret, He Jiankui ignored the ethical consensus against human germline genome editing. Due to this incident, regulations about when and how related research should be use in clinical treatment are being discussed and issued. Moreover, there have been even calls for a moratorium of clinical use of human germline editing.

    Although still experimental, it is expected that one day CRISPR would arrive to the market. This creates another controversial set of issues. Who will have access to it? Would the cost be prohibitive for most people?  Would CRISPR be similar to many new cancer or other high-tech medications and therapies with quite expensive price tags? Would CRISPR be seen as a discrimination tool via the market? These are open questions with no simple answers.

    Beyond the ethical concerns, people may tend, out of fear, to magnify some drawbacks and minimize important merits (or vice versa) and so, could be sensitive to rumors or unprecise information. That is the case of non-therapeutic uses of CRISPR. The idea that CRISPR could be used for frivolous ends (i.e., phenotype “corrections” like cosmetic surgery for aesthetics) is a frequent misconception about what CRISPR could do.  In general, it should be mentioned that the state of arts in genetics is not quite there yet to attempt any phenotype “correction.”  Simply put, science does not know exactly what the consequences are of changing some genes.


    In conclusion, editing CRISPR genome allows scientists to quickly create cell, which can be used to accelerate research into diseases such as cancer and mental illness. Also, CRISPR is now being developed as a rapid diagnostic tool.  However, CRISPR is still in its early days of and there are still scientific and ethical limitations to take into consideration


    Resources


  • I don’t know it when I see one

    I don’t know it when I see one

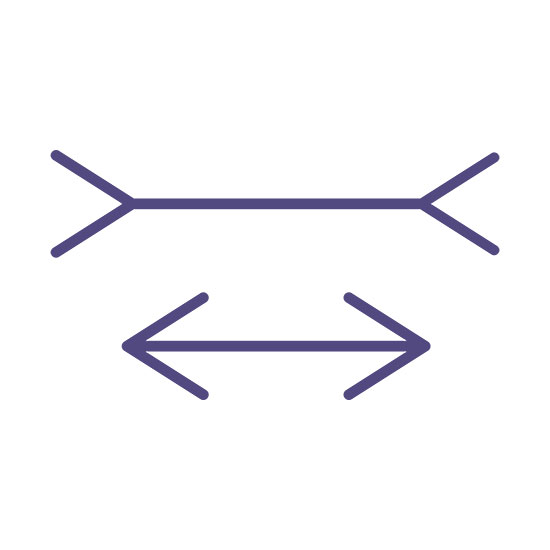
    In Fig. 1, which line is longer?

    Fig. 1 Müller-Lyer illusion

    Our eyes will tell us that the first line seems longer than the second, but in fact two lines are the same. This famous image consisting of stylized arrows is called Müller-Lyer illusion. When we see the picture, though we are asked to place a mark on the figure at the midpoint, our perception will automatically place our vision more towards the “tail end”. Illusions are situations when human’s perception differs from generating stimulus in a meaningful, even misleading way.

    Optical illusions are fascinating, and sometimes even challenging because they demonstrate that what we see is just what we perceive through eyes: we receive the information, interpreted it and yielded the internal representation of the world.

    Psychologists and evolutionary biologists have researched the proposition of illusory perceptual discrepancies. The direction of these researches has been changed throughout history, from purely concentration on the phenomena to the predicted analysis. With enough knowledge of the nervous system, detailed researches of neural structure and function in perspectives of the behavioral research proceed to geometrical and physical directions.

    We can classify illusions into six categories: Luminance and contrast, Motion, Geometric or angle illusions, 3D interpretation (impossible figures), Cognitive effects and Color. Here are some examples related with some of these categories.

    Luminance and contrast

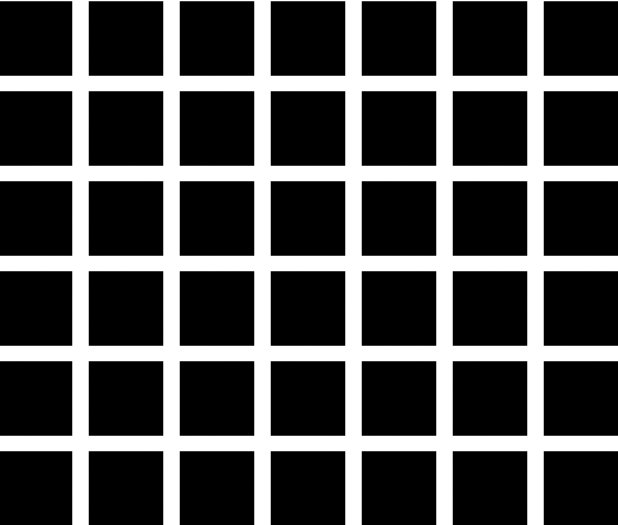
    Fig. 2 Hermann Grid

    The “Hermann Grid” (Fig. 2) is that if you examine the picture, you will see gray dots at the intersections of the white “streets”. This was explained on the concept of lateral inhibition. We see the worlds as our retinal ganglion cells encode and thereby compress it. Moreover, the appearance of gray patches highlights the additional role of cortical processing, i.e. orientation selective neurons.

    Motions

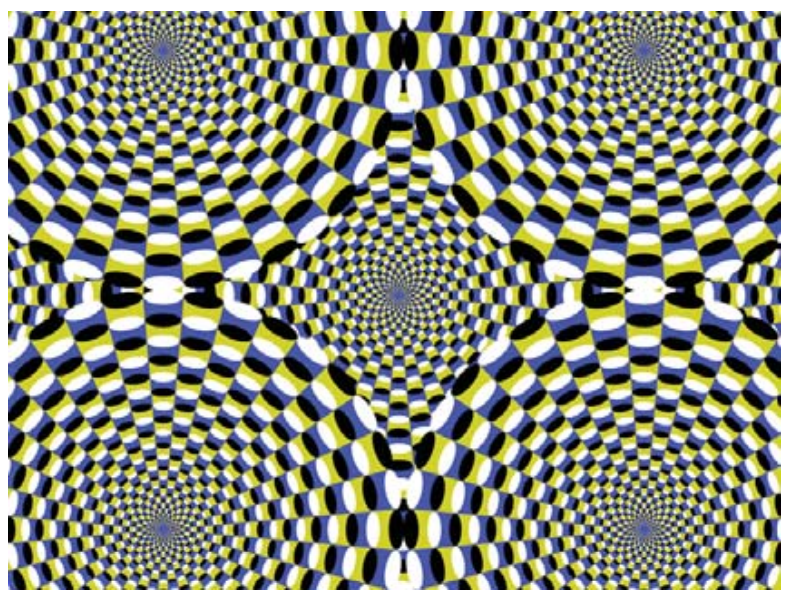
    Fig. 3 Kitaoka’s illusion

    In Fig. 3 the disks seem to expand slowly. One explanation is that when the asymmetric luminance (black to gray to white) appears, we will perceive the asymmetric luminance steps drive motion detectors. Meanwhile, human’s eye movements affect the modulation with our automatic adaptation or possible suppression.

    Geometric or angle illusions

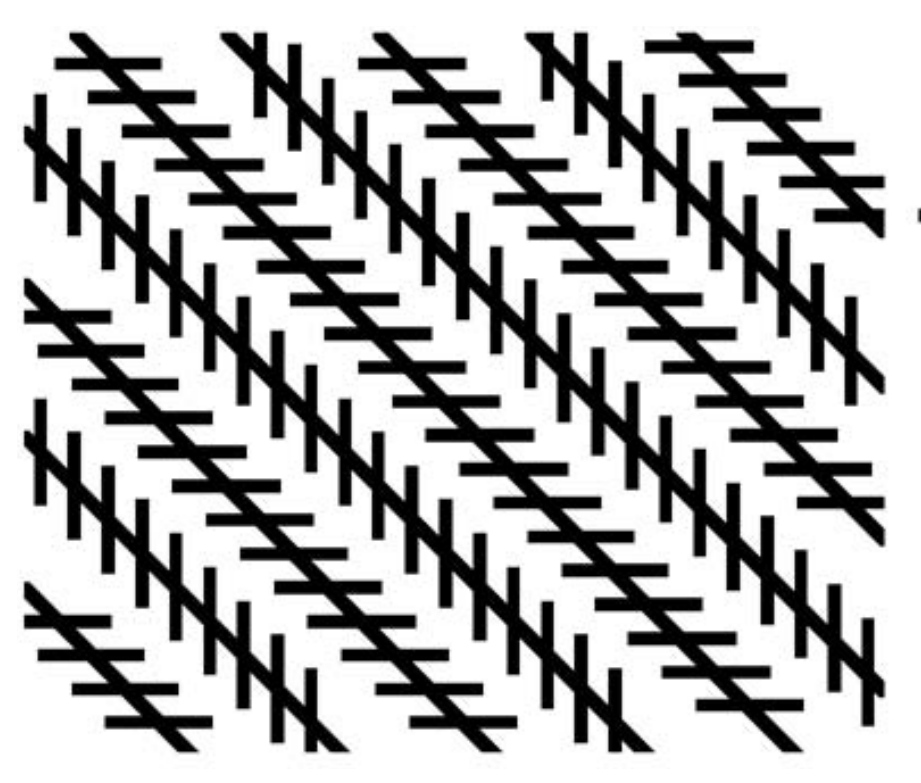
    Fig. 4 J Zöllner illusion

    As J Zöllner discovered in 1860 (Fig. 4), the parallel lines intersected by short lines with right angles appear to be unparalleled. One illustration was that we feel like these parallel lines appear to be closer because we overestimated the small angles affected by the crossings of short lines.

    Impossible figures

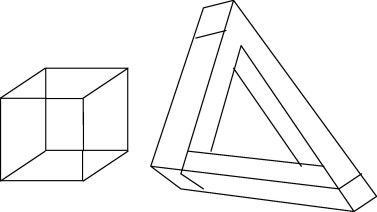
    Fig. 5 Penrose illusion

    As Gerald mentioned (2, Gerald), compared with common cube, figures of the Penrose (Fig. 5) and Escher type require specific parsing of the figure’s components and deductive reasoning to reveal the impossibility of their physical realization. These so-called “impossible figures” require human beings to imagine a physical world, take time to simulate and get a perception, but in fact neglect some other sensory. Basically, they can be created through illusory contours, time discrepancies and perspective drawings.


    Reference:

    Bach, Michael, and Ch M. Poloschek. “Optical illusions.” Adv Clin Neurosci Rehabil 6.2 (2006): 20-21.

    Westheimer, Gerald. “Illusions in the spatial sense of the eye: Geometrical–optical illusions and the neural representation of space.” Vision research 48.20 (2008): 2128-2142.

    Coren, Stanley, and Joan S. Girgus. Seeing is deceiving: The psychology of visual illusions. Lawrence Erlbaum, 1978.